Chondromyxoid Fibroma
Chondromyxoid fibroma is a rare benign bone tumor that is most commonly found in the metaphysis of adolescents and young adults. It consists of components that resemble cartilage (“chondro”), gelatinous matrix (“myxoid”), and fibrous tissue. Approximately one-third of chondromyxoid fibromas occur about the knee, particularly the proximal tibia, while a smaller percentage develop in the tubular bones of the hands and feet. Although chondromyxoid fibroma is considered benign, it can be locally aggressive and has a 25% local recurrence rate following intralesional curettage.
Epidemiology
Chondromyxoid fibroma accounts for approximately 1% of all bone tumors. The majority of cases occur in patients in their first two decades of life, although a second peak of cases has been reported among patients aged 50-70. Surface-based chondromyxoid fibromas are more common in older patients.
Clinical Features
Chondromyxoid fibroma typically presents with deep bone pain, often worse at night. Patients may also experience swelling or a palpable mass at the site of the tumor. In rare instances, the tumor may cause a pathological fracture. However, some patients with chondromyxoid fibroma can also be asymptomatic, with the tumor discovered incidentally on imaging studies.
Radiologic Features
On plain radiographs, chondromyxoid fibroma appears as an eccentric, metaphyseal, radiolucent lesion. Although the majority of tumors develop within the medullary space, surface-based tumors exist and can be confused with periosteal chondroma or other juxtacortical neoplasms.
Chondromyxoid fibromas have a geographic margin with a narrow zone of transition and usually thin surrounding sclerosis. They can also cause thinning or expansion of the neighboring cortex. They have a multichambered appearance due to the well-demarcated sclerotic rim that runs around and within the lesion (Figure 1). Matrix mineralization is not usually seen radiographically, but subtle, stippled calcifications can be seen on computed tomography.

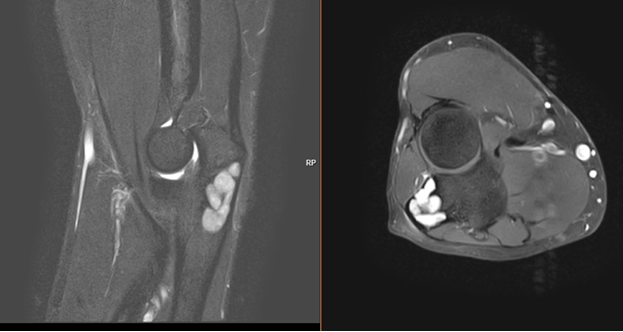
MRI demonstrates isointensity to muscle on T1-weighted sequences and hyperintensity on fluid-sensitive sequences due to the high water content of chondroid and myxoid tissues. Calcified areas appear hypointense on both T1- and T2-weighted sequences. The enhancement pattern of the lesion is unpredictable, and can be heterogeneous (Figure 2).
Pathology
Grossly, the tumor is sharply demarcated and surrounded by a thin layer of bone or periosteum. Microscopically, the tumor consists of hypocellular lobules of chondroid matrix surrounding benign-appearing spindle-shaped cells that typically are not within lacunae (Figure 3). Giant cells can be seen scattered throughout the matrix and hypercellular fibroblastic septa can be seen running between the lobules. Although mild nuclear pleomorphism can be present, mitotic figures are rare.

The spindle cells within the chondroid matrix of chondromyxoid fibroma can stain weakly positive for S100 protein, a low-molecular-weight calcium-binding protein. This, however, is a non-specific finding.
Chondromyxoid fibroma is now characterized by upregulation/rearrangement of the GRM1 gene (glutamate metabotropic receptor 1), and GRM1 immunohistochemistry has emerged as a useful diagnostic marker distinguishing CMF from its mimics.
Differential Diagnosis
Radiologically, the differential diagnosis for chondromyxoid fibroma depends on location but includes many lucent bone lesions. Centrally based lesions can be confused with non-ossifying fibroma, osteoblastoma, aneurysmal bone cyst, chondroblastoma, giant cell tumor of bone, and chondrosarcoma. Surface based lesions can be mistaken for juxtacortical chondroma, cortically based chondrosarcoma, and non-ossifying fibroma.
Malignant bone tumors such as osteosarcoma and Ewing sarcoma may also be considered in the differential diagnosis, but malignancies usually have more aggressive radiographic features (e.g., periosteal reaction, absence of a sclerotic rim).
Histologically, chondromyxoid fibromas can resemble chondrosarcoma, enchondroma, or chondroblastoma due to their locally aggressive behavior and cartilage/myxoid matrix.
Disease Course: Treatment and Prognosis
The goal of treatment is to remove the tumor and prevent recurrence. Surgical excision with intra-lesional curettage is the primary treatment for chondromyxoid fibroma. This curettage can be augmented by other local treatment such as burring, cautery, and other local adjuvants. Bone graft or cement can be used to fill the defect. Curettage alone has a high recurrence, up to 80%, whereas extended curettage with adjuvants and grafting has a recurrence rate far lower,10% –33%. The local recurrence rate in younger patients may not be lowered by local adjuvants. For this reason, wide en bloc resection of the lesion may occasionally be necessary.
Key Test Topics
Chondromyxoid fibroma has a lobulated, multiphasic appearance on histology.
A purely lytic lesion in the metaphysis of young patients, especially in the proximal tibia, suggests chondromyxoid fibroma. Think of it as looking like a large NOF.
Treatment is intralesional curettage, typically augmented by local adjuvants and bone grafting or cement.