Fibromatosis, desmoid tumor and desmoplastic fibroma of bone
Fibromatosis is a generic term for multiple conditions that involve the development of a benign, locally aggressive fibroblastic tumor in an inter- or intramuscular location. On the plantar surface of the foot, this condition is known as Ledderhose’s Disease or Plantar Fibromatosis. On the penis, it is called Peyronie’s disease, and on the palm, it is called a Dupuytren’s contracture.
The term “desmoid tumor” is used when fibromatosis develops in soft tissue locations other than those listed above. When a tumor with similar histology develops in bone, it is called a desmoplastic fibroma of bone. Desmoplastic fibromas of bone are rare, benign but locally destructive and variably aggressive lesions.
Desmoid tumors are characterized by abundant collagen and fibroblastic cells that infiltrate the surrounding muscle. They are benign with no malignant transformation potential (unless radiated), however they can grow rapidly and invade surrounding structures. Due to the infiltrative growth pattern, complete “margin-negative” wide surgical resection can be difficult to achieve and even if achieved, is associated with a high local recurrence rate. As such, surgical procedures can be technically challenging and extremely morbid and still have a high rate of local recurrence. For this reason, multiple medical treatment regimens have been proposed and surgery is no longer recommended as first line treatment. Observation is usually listed as the most favorable first line treatment although a majority of patients will subsequently require further treatment.
Epidemiology
Desmoid tumors develop at a rate of 3-4 cases per million people per year and are typically diagnosed in adolescents and young adults. These lesions are less common in patients over the age of 35.
Approximately 1,000 new cases are diagnosed per year in the United States. These lesions are more frequently seen in females (3:1) and can develop as a solitary desmoid, or as a collection of multiple lesions, usually within the same extremity.
Clinical Features
Desmoid tumors develop within the superficial or deep muscles, often associated with fascia. Their most common locations are the shoulder, torso, and thigh. The high collagen component and intimate interdigitation with surrounding muscles cause desmoid tumors to feel immobile and “hard as a rock” on physical exam. Desmoid tumors can be locally painful, and compression of nearby neurovascular structures can cause neuropathic pain or swelling distal to the tumor itself.
Desmoid tumors tend to grow for a period of time and follow an unpredictable course. A small portion will spontaneously resolve without treatment. Some will expand to a point and then stop growing, and some will continue to grow unless treated. Given the possibility of spontaneous stability or regression, observation is a reasonable first line of treatment although this is frequently not successful necessitating more specific treatment.
Radiologic Features
Desmoids are soft tissue tumors without calcifications, therefore radiographs play a minimal role in diagnosis. Occasionally, the tumor will cause pressure erosion on a neighboring bone, which will be the only radiographic abnormality detectable on an x-ray.
CT scans are not good at delineating these tumors as they appear similar to normal muscle. MRI is the most diagnostically useful imaging study for desmoid fibromatosis. On T1 imaging, the tumor is primarily isointense to muscle, consistent with most soft tissue tumors, it may also demonstrate thick bands of lower signal, representing the prominent collagenization. This high collagen content also explains a heterogeneous, and relatively low, signal intensity is seen on fluid-sensitive sequences such as fat-saturated T2, or STIR. This is a key imaging characteristic that helps to recognize a desmoid tumor from other soft tissue masses though these findings are not diagnostic.
Another differentiating quality of desmoids is the irregular, infiltrative, non-geographic border between the tumor and surrounding muscle on MRI. Desmoid tumors exhibit an infiltrative growth pattern, unlike most soft tissue tumors, indicated by the infiltrative margin at the tumor-muscle interface (Figure 1 and Figure 2). On post-contrast images, desmoids display an unpredictable but frequently heterogeneous enhancement pattern.


When the process of fibromatosis occurs primarily in a bone, the condition is known as a desmoplastic fibroma of bone (Figure 3). These lesions are well-characterized on radiographs, which reveal trabeculated, expansile, and radiolucent bone lesions often with lobulated margins. These locally aggressive bone tumors may erode through the cortex and have an associated soft tissue mass.

Pathology
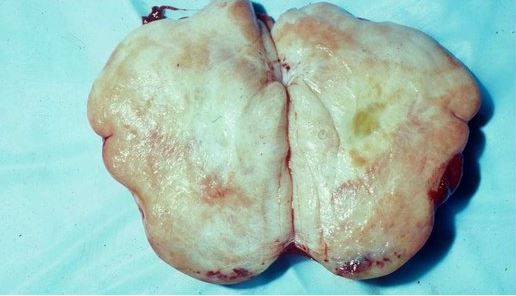
Grossly, desmoid tumors are poorly-circumscribed, infiltrative masses that vary from pink to gray-white in color, and from firm to rock-hard in consistency. There is no capsule or pseudocapsule at the periphery. They are relatively hypovascular and often appear to be a mass resembling fibrous scar tissue (Figure 4).
Histologically, bundles of uniform, elongated spindle cells weave amongst abundant collagen. The spindle cells show no atypia or pleomorphism, even on a higher power view. At the margin with neighboring muscle, the tumor cells can be seen invading the muscle fibers (Figure 5). These tumors stain positively for estrogen receptor beta and nuclear β-catenin with the latter being diagnostic for desmoid tumor.

Recent genetic analysis of desmoplastic fibroma of bone has demonstrated that although its infiltrative pattern of growth resembles that of desmoids histologically, they lack the mutation in exon 3 of CTNNB1 that encodes for β-catenin as seen in desmoid tumors. As such, it is best to consider desmoplastic fibroma of bone not merely as osseous counterpart to desmoid tumors but as genetically distinct entity.
Fibromatosis has been associated with Familial Adenomatous Polyposis (also known as Gardner syndrome) and this is due to a common underlying gene mutation that drives both disorders, namely, that of the β-catenin gene. Desmoids commonly demonstrate estrogen receptor positivity, but this has not been utilized successfully via hormonal treatment.
Differential Diagnosis
Desmoid tumors tend to be harder than other soft tissue lesions when palpated on physical exam, but this finding is not sufficiently reliable for diagnosis.
As noted, desmoid tumors have two characteristic MRI findings that will aid in their diagnosis, relative hypointensity on fluid-sensitive imaging and an infiltrative growth pattern with indistinct margins. However, these features are neither pathognomonic nor always demonstrated. Therefore, the diagnosis of a desmoid cannot be definitively established on imaging, and biopsy is necessary for histologic diagnosis.
The differential diagnosis for desmoid fibromatosis in most locations includes most benign and malignant soft tissue tumors.
Desmoplastic fibroma of bone likewise cannot be definitively diagnosed with imaging studies, as many bone tumors can cause lucency with cortical destruction. Here, the differential diagnosis includes fibrous dysplasia, simple bone cyst, aneurysmal bone cyst, chondromyxoid fibroma and bone sarcomas.
Disease Course: Treatment and Prognosis
Treatment strategies for desmoid fibromatosis include observation, surgery, chemotherapy, hormonal therapy, and radiation therapy, either individually or in combination.
Local recurrence is reported to be approximately 40% or higher when positive-margin excision is performed. Wide-margin resections often involve large amounts of muscle being resected, with subsequent dysfunction and disfigurement and is still associated with a high recurrence rate. Even extensive resection does not always prevent local recurrence, given the tumor’s infiltrative growth pattern. In light of this, surgery is no longer a mainstay of treatment unless the lesion is small and can be removed with minimal morbidity.
Historically, high-dose radiation was combined with wide margin surgery to reduce the local recurrence rate. In recent years, radiation has been avoided, due to its propensity to cause malignant transformation. As a result, several relatively effective medical treatment options have replaced surgical resection as the first-line treatment for desmoid fibromatosis.
Medical management exists on a spectrum of off-setting effectiveness and morbidity. The easiest and least morbid treatment option is non-steroidal anti-inflammatory drugs such as sulindac, or more recently, meloxicam. These drugs may induce partial responses and may control symptoms enough to be satisfying to patients.
Other medical strategies include low-dose chemotherapy with methotrexate and either vinblastine or vinorelbine. Low-dose chemotherapy has been reported to provide reliable symptom relief, at least partial response (if not complete regression) in over half of patients, and 70% relapse-free interval with a median of 10 years. Importantly, this low-dose chemotherapy regimen was not associated with significant adverse side effects, as other combinations involving doxorubicin tend to have.
Hormonal therapies such as tamoxifen can be tried, either as a frontline treatment or after other approaches have failed. While head-to-head data is limited, Tamoxifen has not shown the efficacy that the methotrexate-vinblastine/vinorelbine combination has. Newer systemic agents have also been shown to be effective against desmoid tumors, inducing tumor stability, partial response, or regression in most cases. Due to desmoid’s expression of PDGF receptors, treatment with the tyrosine kinase inhibitor imatinib mesylate has been shown to induce at least partial response and improve quality of life. The multitargeted oral tyrosine kinase inhibitor sorafenib has more recently been shown to result in tumor shrinkage and symptom relief to a greater degree than imatinib. Recently, the gamma-secretase inhibitor nirogecestat has also shown anti-tumor activity. The net result is that no drug therapy has been 100% successful and many patients will need to be treated with a variety of drug therapies over time.
Key Test Topics
- Rock-hard to palpation on physical exam
- Imaging characteristics: infiltrative margin, hypointensity on T1 and fat suppressed T2
- Surgical resection is no longer the standard of care due to the infiltrative growth pattern leading to morbid wide resections and high local recurrence rate, first line treatment is observation followed by medical management if observation reveals tumor progression.
- No malignant transformation unless radiated.
- Staining pattern: estrogen receptor-beta, beta-catenin
- Associated with familial adenomatous polyposis (Gardner Syndrome)