A Systematic Approach to Soft Tissue Tumor Pathology
A (somewhat) simplified approach to the diagnosis of soft tissue tumors
Soft tissue tumors present a significant challenge to clinicians as well as surgical pathologists for the following reasons:
- Many are rare
- Their morphology frequently overlaps
- Some sarcomas maintain a bland histologic appearance which belies their malignant behavior
- Some benign tumors mimic their sarcoma counterparts.
Benign and malignant soft tissue tumors form a large array of individual lesions requiring significant histologic, immunohistochemical, and genetic investigation to delineate. It is beyond the intent of this chapter to enable the reader to understand the more detailed issues associated with each of these tumors. It is possible however to create an algorithmic approach to the most common lesions and in so doing to narrow the histologic differential diagnosis for any particular tumor encountered. While this presentation is still somewhat complex, it is as simplified as we could make it. There is a lot of information here. Considering this complexity, we included a summary at the end of the chapter to help clarify this approach to soft tissue tumor histology.
To simplify the differential diagnostic approach, we break down the most common soft tissue tumors using two lines of differentiation. The first is the predominant morphologic pattern including the shape, size and appearance of the cells on the pathology slide. This is followed by the second, the lineage of differentiation utilizing the assistance of immunohistochemistry (IHC). This investigates markers on the cell surface or within the nucleus or cytoplasm (for example, lipo-, angio-, neuro-, fibro-, leio-, rhabdo-, or undetermined).
The morphologic patterns are not mutually exclusive and certain tumors may display more than one morphologic pattern. To simplify this somewhat, consider the morphologic pattern and then the lineage of differentiation as defined by immunohistochemical (IHC) markers, as shown in the following table:

1. Lipomatous Morphologic Pattern
Most lipomatous tumors are easily recognizable given their adipocytes and/or lipoblasts mixed with other elements. Adipocytes are immunoreactive to S100, although this is usually unnecessary to perform due to their distinct morphology.
Benign:
A. Lipoma and lipoma variants – (spindle cell, fibro-, angio-, myelo-)
These tumors contain uniform benign appearing fatty tissue. Benign lipomas are easy to diagnose and can be reliably diagnosed with MRI or CT scan even without histological sampling. A uniform fat density lesion which follows adjacent normal fat on all sequences (e.g. on MRI-uniformly bright when the fat is bright and uniformly dark when the fat is dark) are almost always benign lipomas although some atypical lipomatous tumors (ALT) may have minimal stranding and resemble a benign lipoma. Histologically, benign lipomas are morphologically indistinguishable from normal adipose tissue, which is composed of back-to-back polyhedral cells filled with a single lipid droplet that pushes the nucleus to the periphery of the cell. We figured that you did not need a picture of benign fat cells! (Remember that the fat in the cells is dissolved by organic solvents during tissue processing, creating empty holes on histology.) (Take away: uniform fat on histology is a benign lipoma.)
Lipoma variants are distinct clinicopathologic entities (angiolipoma, spindle cell lipoma, myelolipoma, fibrolipoma, hibernoma etc.), which contain a significant second component in addition to mature adipose tissue morphologically. Angiolipoma is composed of mature adipose tissue with clusters of capillaries at the periphery plugged with fibrin thrombi (Figure 1A, see arrows). The presence of these fibrin thrombi is required for diagnosis. Spindle cell lipoma is characterized by adipose tissue admixed with bland spindle cells and ropey collagen bundles (Figure 1B, see arrow for ropey collagen bundle). Myelolipoma consists of mature adipose tissue and marrow components resembling normal bone marrow (Figure 1C). Hibernoma is composed of brown fat. Brown adipocytes have numerous small cytoplasmic vacuoles indenting the nuclei histologically and render a foamy appearance (Figure 1D). Hibernomas have varying numbers of these foamy cells (Take away: Uniform fat with one of the additional components listed above makes a lipoma variant.)

Intermediate (locally aggressive):
B. Atypical lipomatous tumor/well-differentiated liposarcoma (ALT/WDL)
On MRI, ALT/WDL is characterized by abundant fatty signal with varying amounts of stranding within the tumor. On histology these tumors are composed mostly of mature fat with some fibrous septa winding through the lobules of fat. Figure 2A demonstrates a low power view with normal appearing adipocytes and fibrous septa. There are scattered neoplastic cells with abnormal large hyperchromatic nuclei and an irregular nuclear contour throughout the tumor. These hyperchromatic cells are commonly found in the fibrous septa or around blood vessels (Figure 2B, see arrows). These abnormal cells can also be present among adipocytes. The stroma or background cells around the adipocytes are more fibrotic compared to a plain lipoma. In the extremities, these tumors are called “atypical lipomatous tumor” (ALT). This is a benign designation because these extremity tumors have never been known to metastasize in the absence of dedifferentiation. This same pathology is termed “well differentiated liposarcoma” (WDL) when located in the retroperitoneum. ALT and WDL share the same genetic abnormality, amplification of gene cluster containing MDM2 and CDK4 on chromosome 12 (forming a giant ring chromosome), which results in protein overexpression. Detection of MDM2 (Figure 2C) and/or CDK4 protein overexpression by IHC can be utilized as a surrogate to gene amplification by fluorescence in situ hybridization (FISH) for diagnosis. ALT/WDL can take a more aggressive disease course compared to ordinary benign lipoma which is why we try to delineate the correct diagnosis. (Take away: Benign appearing fat with intervening fibrous septa, hyperchromatic atypical cells and MDM2 (and/or CDK4) amplification defines an Atypical Lipomatous Tumor seen in the extremities or a Well-Differentiated Liposarcoma seen in the retroperitoneum.)
Malignant: Malignant tumors of lipomatous differentiation comprise the family of liposarcomas. There are several subtypes.
C. Myxoid liposarcoma / round cell liposarcoma
These tumors constitute a spectrum of the same disease, morphologically characterized by signet ring lipoblasts, monomorphic round cells, myxoid stroma and an arborizing capillary network (Figure 2D, low grade, low power). (You need to be able to recognize a lipoblast which is a large fat containing cell with an eccentric nucleus pushed to the periphery of the cell by the cytoplasm. These are also called “signet ring cells” (arrow heads) because they look like a college ring on its side.) When the round cell component is more than 5% of the tumor (hypercellular areas composed of back-to-back round blue cells with scant cytoplasm), the tumor is deemed round cell liposarcoma (Figure 2E), which is a high-grade tumor with a higher risk of distant metastasis and hence, a worse prognosis. Myxoid liposarcoma and round cell liposarcoma share the same chromosome translocation t (12, 16) resulting in the fusion gene FUS-DDIT3. FISH study for the DDIT3 gene translocation can be used for confirmation of the diagnosis. (Take away: Lipoblasts, round cells, myxoid stroma and an arborizing capillary network define myxoid liposarcoma which merges into round cell liposarcoma if the round cell component is more than 5%).
D. Pleomorphic liposarcoma
A rare (<5% of all liposarcoma) aggressive sarcoma. It is a highly pleomorphic sarcoma containing numerous pleomorphic lipoblasts with cytoplasmic vacuoles indenting nuclei (Figure 2F, arrow shows pleomorphic lipoblast). (Take away: Pleomorphic tumor demonstrating pleomorphic lipoblasts.)
More advanced discussion regarding malignant lipomatous tumor
E. Dedifferentiated liposarcoma (DDL)
Dedifferentiated liposarcoma is within the morphologic spectrum of the same disease as ALT/WDL characterized by MDM2/CDK4 gene amplification. In DDL, the high-grade component typically has the appearance of an undifferentiated pleomorphic spindle cell sarcoma with minor or no lipogenic component (Figure 2G). The tumor cells can be spindle-shaped or epithelioid with scattered large, atypical cells as seen in ALT/WDL. When it demonstrates a lack of adipocytic phenotype (especially on a biopsy), it poses a great challenge to diagnosis, which hinges on detection of the amplification of MDM2/CDK4 by FISH or IHC. An accurate diagnosis requires the pathologist to be vigilant to search for any minor residual lipogenic component and readily performing MDM2/CDK4 IHC when confronted with a pleomorphic spindle cell sarcoma in specific locations where ALT/WDL commonly develop (such as the extremities and retroperitoneum). (Take away: This tumor is composed of an ALT or WDL which has dedifferentiated into an undifferentiated tumor with these areas frequently looking like UPS. The underlying ALT/WDL may be difficult to find. Need to see MDM2 staining to make the diagnosis if the underlying ALT or WDL is not obvious)

2. Vascular Morphologic Pattern
These show a network of irregular vascular spaces many of which contain blood.
Benign:
A. Hemangioma and other non-neoplastic lesions
Benign vascular lesions include reactive lesions, malformations or neoplasms such as hemangioma that are characterized by a network of vascular spaces (Figure 3A). Common reactive vascular lesions include granulation tissue and papillary endothelial hyperplasia which are reparative processes where capillary proliferation is an inherent part. Vascular malformations are a spectrum of malformed vascular channels made of arteries, veins or a combination of both (arteriovenous malformation (Figure 3B)). Hemangiomas are bona fide benign vascular neoplasms, which may range from large venous lakes to abnormal thin-walled capillaries. Distinguishing among various types of benign vascular lesions can be difficult and subjective. The immunohistochemical markers for the vascular lesions are CD31 and ERG, which can be used to confirm vascular origin of the lesion when in doubt. (Take away: Histologic appearance of benign vascular elements including arteries, veins or capillaries showing CD31 or ERG positivity.)
Malignant:
B. Angiosarcoma
Angiosarcomas (Figures 3C through 3E) are malignant tumors of mesenchymal cells demonstrating vascular differentiation. They are usually hemorrhagic lesions because of their defective vasoformative nature. The malignant behavior can be assessed from three aspects histologically: 1. infiltrative growth pattern: instead of the lobular growth pattern of benign vascular tumors, angiosarcoma cuts through and entraps surrounding normal soft tissue; 2. architectural complexity: instead of forming a single layer of endothelial cells, angiosarcoma tends to form complex anastomosing vascular networks and to pile up on each other; 3. cytologic atypia: nuclei tend to be pleomorphic and hyperchromatic (dark), and stick out or protrude along the vascular lumen (hobnail pattern). These tumors typically stain strongly with IHC vascular marker stains CD31 and ERG (Take away: Angiosarcoma is identified by complex anastomosing vascular channels with pleomorphic hyperchromatic cells and CD31 or ERG positivity.)

3. Spindle Cell Morphologic Pattern:
These tumor cells primarily demonstrate an elongated shape and tapered ends but having said that, these tumors resemble one another to a high degree so that Immunohistochemistry (IHC) is usually needed to make a specific histologic diagnosis. Adult-type fibrosarcoma is a prototypical example of a spindle cell sarcoma, which demonstrates a highly cellular fibroblastic proliferation in a herringbone pattern (spindle cells arranged in fascicles intersecting at acute angles). However, adult-type fibrosarcoma has become exceedingly rare, almost extinct, because they are now reclassified as other more distinct entities. The term “Fibrosarcoma” is no longer commonly used but is still occasionally utilized as an umbrella term to describe all the sarcomas of fibroblastic origin, particularly those with a herringbone growth pattern.
Again, because there is significant morphologic overlap between these different spindle cell morphologic entities, it is difficult, if not impossible, to render an accurate diagnosis relying solely on histo-morphologic assessment. Therefore, IHC is now almost always used to accurately determine the lines of differentiation (cell of origin) of spindle cell tumors. Spindle cell tumors mainly consist of peripheral nerve sheath cell (neuro-), smooth muscle (leio-), skeletal muscle (rhabdo-), (myo)fibroblast (fibro-), or undetermined cell of origin based on their lineage differentiation.
A. Neural phenotype
Neoplasms arising from peripheral nerve sheath cells (Schwann cells or perineurial cells).
Benign – always demonstrate strong and diffuse S100 immunoreactivity.
a. Schwannoma
This tumor demonstrates long spindle cells with wavy tapered nuclei and indistinct pink cytoplasm. The classic finding in this tumor is the presence of Antoni A (high cellularity) and Antoni B (low cellularity) areas, palisading nuclei aligned along an anuclear zone (called a Verocay body) in the Antoni A area, as well as thick-walled hyalinized blood vessels (Figure 4A). (Take away: strong S100 positivity, Antoni A and B areas, palisading nuclei, Verocay bodies and thick-walled hyalinized blood vessels.)
b. Neurofibroma
This tumor consists of mixed cell types: Schwann cells and fibroblasts, in contrast to schwannoma composed of only Schwann cells. Neurofibromas demonstrate randomly oriented spindle cells with wavy dark nuclei and characteristic collagen bundles having the appearance of shredded carrots (Figure 4B). Both schwannomas and neurofibromas stain strongly with S100 due to their strong neural phenotype (Figure 4C) (Take away: Spindle cells with wavy dark nuclei and collagen bundles that look like shredded carrots strongly positive for S100.)
Malignant – Variable S100 immunoreactivity because these tumors are dedifferentiating and losing their normal neural phenotype (S100 staining can often be completely negative or patchy/focal, but not strong and diffuse, except for epithelioid MPNST).
c. Malignant peripheral nerve sheath tumor (MPNST)
Most MPNSTs are high-grade malignancies and occur most often in three clinical settings: associated with large nerves, a history of radiation and neurofibromatosis 1 syndrome. These tumors are hypercellular spindle cell sarcomas arranged in dense fascicles intersecting at acute angles (herringbone pattern, Figure 4D). When the fascicles alternate with myxoid areas, a marble-like pattern can be seen at low magnification. There is usually a moderate degree of cytologic atypia, nuclear hyperchromasia and enlargement. Geographic necrosis is characteristic and heterologous elements (aberrant differentiation into bone, cartilage, skeletal muscle and epithelial glands etc.) are present in 10-15% of tumors. (Take away: Hypercellular spindle cell sarcomas, often with some marbled myxoid areas and hope for some S100 positivity to make the diagnosis clear.)
B. Smooth muscle tumors
Elongated spindle cells with abundant eosinophilic cytoplasm running in fascicles which intersect at right angles (Figure 4E). Nuclei show blunted ends (cigar shaped) and perinuclear vacuoles. Smooth muscle tumors should demonstrate strong and diffuse immunoreactivity to desmin (Figure 4F) and/or Smooth Muscle Actin (SMA). SMA is also positive in (myo) fibroblasts and is not as specific as desmin. (Take away: Benign or malignant tumors with elongated spindle cells with cigar shaped nuclei and strong reactivity to desmin or SMA.)

Benign
a. Leiomyomas and variants
These are extremely common in the uterus, but much less commonly seen in soft tissue and skin. Outside the uterus, they are believed to arise from the smooth muscle cells of blood vessels (angioleiomyoma) or pili erector muscle in the skin (cutaneous leiomyoma) at these uncommon locations. Leiomyomas outside of the gynecologic tract should demonstrate minimal cytologic atypia, no necrosis, and very low mitotic activity (< 1 mitotic figure / 50 HPF). These tumors are difficult to recognize histologically so positive staining with desmin and SMA are critical to making the diagnosis
Malignant
b. Leiomyosarcoma
These are defined by significant pleomorphism (similar to but typically less than UPS), increased mitotic rate (> 1 mitotic figure / 10 HPF) and/or tumor necrosis. Leiomyosarcomas of soft tissue are uncommon. The top three locations are retroperitoneum, large blood vessels and lower extremities.
Cutaneous leiomyosarcoma, a special variant showing morphology similar to leiomyosarcomas of other locations, has an excellent prognosis (almost no distant metastasis) because of their superficial location and limited clinical stage. Thus, they were recently reclassified as “atypical intradermal smooth muscle neoplasm” by WHO. As with leiomyomas, this diagnosis is difficult to make histologically so again, look for desmin and SMA positivity. (Take away: Benign or malignant spindle cell tumors with desmin and SMA positivity)
C. Skeletal muscle tumors
In addition to strong and diffuse immunoreactivity to desmin, tumor of striated muscle origin should be reactive to other lineage specific markers such as myoD1 and/or myogenin, whose positivity can often be limited to a small subset of cells. (Take away: Benign or malignant tumors with strong positivity to desmin but also to myoD1 and/or myogenin.)
Benign
a. Rhabdomyomas
Benign skeletal muscle tumors are much less common than their malignant counterparts, accounting for less than 2% of all tumors of striated muscle origin. There are several different subtypes (cardiac, adult, fetal and genital) associated with distinct clinical settings. Fetal and genital rhabdomyomas take the form of spindle cell morphology with abundant eosinophilic cytoplasm composed of myofibril fibers. Adult (mainly in head and neck area) and cardiac rhabdomyoma cells usually demonstrate polygonal shape rather than spindled morphology (Figure 5A). Cross-striations are a hallmark of rhabdomyomatous tumors and mimic those which are seen in normal striated muscles.
Malignant
b. Rhabdomyosarcomas
WHO recognizes four subtypes of rhabdomyosarcomas: embryonal (Figure 5B), alveolar (pictured in fig. 8-D under discussion of the round cell morphologic pattern), pleomorphic, and spindle/sclerosing (Figure 5C). All Rhabdomyosarcomas show positive staining for the muscle markers Myogenin (Figure 5D) and Myo-D. Embryonal rhabdomyosarcomas occur mainly in young children while alveolar rhabdomyosarcomas typically affect adolescents and young adults. Pleomorphic rhabdomyosarcoma is most common in the sixth to seventh decades of life. Spindle cell/sclerosing rhabdomyosarcoma affects both children and adults. Embryonal and spindle cell/sclerosing rhabdomyosarcomas demonstrate spindle cell morphology, while alveolar rhabdomyosarcoma consists of round blue tumor cells (see round cell pattern). Pleomorphic rhabdomyosarcoma (Figure 5E) shows striking cytologic atypia with admixture of spindled and rounded cells. (No easy take away but consider the following: small round blue cell tumors showing skeletal muscle lineage with positive staining for the skeletal muscle markers desmin, myogenin and MyoD1. Embryonal in children under age 15, alveolar and pleomorphic in older children and young adults.)
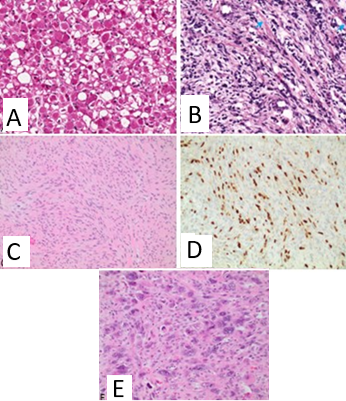
D. Fibrous Tumors
Neoplasms arising from myofibroblasts, are a heterogeneous group of tumors demonstrating a wide array of histomorphology. Histologic clues suggesting a tumor is of myofibroblastic origin are spindled morphology with pale-staining oval nuclei, lightly basophilic pointy cytoplasm, and abundant collagen matrix. No specific immunohistochemical stain can be used to prove their lineage identities. However, positive immunoreactivity to smooth muscle actin (SMA) is supportive of myofibroblast origin, particularly if in a tram-track staining pattern wherein SMA+ actin filaments are seen in parallel lines in the cytoplasm because they are concentrated along a cell membrane (Figure 6A). Selective representative entities are described in three categories, benign/pseudotumor, locally aggressive but non-metastasizing, and malignant. (Take away: Spindle cell tumor with eosinophilic (pink) collagen present in the extracellular matrix, SMA positivity and tram-track staining pattern.)
Benign
a. Nodular fasciitis
This was once believed to be a reactive process. However, its clonal neoplastic nature has been established via identification of recurrent USP6 gene translocations. Nodular fasciitis is a self-limited neoplasm and greatly mimics sarcoma due to its conspicuous mitotic activity and rapid growth rate in the first six months. Histologically, nodular fasciitis demonstrates bland spindle cells loosely arranged in a feathery or tissue culture pattern (Figure 6B). The stroma can vary from myxoid to hyalinized depending upon the age of the tumor. Mucinous pool and RBC extravasation are characteristic histologic features. FISH study for USP6 gene rearrangement is a very helpful confirmatory test, particularly for uncertain cases or those with a small biopsy. (Take away: fast growing spindle cell tumor which is benign but mimics malignancy due to its high mitotic activity. Look for a FISH study demonstrating a USP6 gene re-arrangement.)
Locally aggressive but non-metastasizing
b. Desmoid-type fibromatosis
This is a locally aggressive neoplasm with no metastatic potential which usually demonstrates an infiltrative growth pattern and can be seen growing into surrounding skeletal muscle. Histologically, it is composed of sweeping fascicles of spindle cells with small slender nuclei and a very fibrotic stroma which is the matrix produced by (myo)fibroblasts (Figure 6C). Desmoid fibromatosis harbors CTNNB1 or APC gene mutations. Nuclear immunoreactivity to beta-catenin (the protein encoded by CTNNB1) is typical and is used as a surrogate marker for these genetic alterations and supports the diagnosis (but cytoplasmic staining is ubiquitously present and does not count). (Take away: histologically benign tumor with spindle cells and abundant collagenous scar-like matrix and nuclear Beta-catenin positivity.)
Malignant
c. Synovial sarcoma
The term “synovial” implies they primarily occur at juxta-articular locations of extremities where synovium can be found rather than referring to their differentiation towards synovium. The differentiation of synovial sarcomas is undetermined, and no evidence is present to support their origin as synovium or as showing differentiation toward synovial cells. Two histologic types are observed for synovial sarcomas: monophasic and biphasic. Unlike most sarcomas which demonstrate only a mesenchymal lineage as shown by vimentin positivity; synovial sarcomas also demonstrate an epithelial component shown by cytokeratin positivity. The monophasic synovial sarcoma is much more common than the biphasic type. These monophasic tumors show a pattern similar to adult fibrosarcoma (herringbone pattern) with monomorphic spindle cells as described above (Figure 6D) but also have an occult epithelial component demonstrated by cytokeratin positivity. In addition to the spindle cell component as in the monophasic type, biphasic synovial sarcomas contain a recognizable epithelial component with a columnar epithelium forming glands (Figure 6E), which can be easily confused histologically with adenocarcinoma. In these tumors the mesenchymal spindle cells will be vimentin positive and the epithelial cells with be cytokeratin positive. TLE1 (Transducer-like enhancer1) is an immunohistochemical marker used by pathologists to identify synovial sarcoma from other sarcomas with a spindled morphology (Figure 6F). Synovial sarcomas consistently harbor specific translocations between SS18 (a.k.a. SYT) and its partner genes (SS1, SS2 or SS4). A FISH study for SS18 translocation can be used to corroborate the diagnosis. (Take away: a biphasic tumor with mesenchymal (vimentin positive) and epithelial (cytokeratin positive) cells. If the epithelial component is not seen histologically but its presence is noted by cells with cytokeratin positivity, it is a monophasic synovial sarcoma. If there is a histologically visible epithelial component with a columnar epithelium forming glands, then it is a biphasic synovial sarcoma. All share the X;18 translocation noted above. TLE1 has become a useful stain for identifying synovial sarcomas.)

4. Myxoid Morphologic pattern:
Myxomatous tumors – tumors demonstrate myxoid stroma (light bluish extracellular matrix as their histologic feature).
Benign
A. Myxoma
This is primarily located in skeletal muscles. It is a markedly hypocellular and hypovascular neoplasm and is predominantly composed of myxoid matrix (this is the second type of matrix produced by (myo) fibroblasts, the other being collagenous matrix). The tumor cells are small stellate to spindle shaped with delicate thin fibers floating around (Figure 7A). (Take away: Benign appearing tumor with few tiny spindle cells and abundant myxoid matrix.)
Malignant
B. Myxofibrosarcoma
A continuum ranging from tumors with some increased cellularity and mild pleomorphism (low grade) all the way through to high-grade tumors with hypercellularity, marked pleomorphism, necrosis, and brisk mitotic activity (Figure 7B). Inhomogeneity is characteristic of these tumors so that hypocellular areas may be intermixed with hypercellular areas. The percentage of myxoid stroma is also highly variable. Tumor cells primarily demonstrate a plump spindled to stellate morphology. There is no specific lineage marker that can be used for a diagnostic purpose. (Take away: a continuum from hypo to hyper cellular with heterogeneous cellularity, pleomorphism and containing a myxoid stroma.)
5. Pleomorphic Morphologic Pattern
Cells in the pleomorphic morphologic pattern of tumors exhibit pronounced variation in size and shape, which is a phenotypic reflection of a very unstable underlying genome (large numbers of copy number changes at both gene and chromosome levels, a.k.a. aneuploid). In contrast, monomorphic sarcomas (minimal variation in size and shape) have a stable diploid genome, and contain a small number of genetic alterations (usually one genetic driver, including a translocation or mutation). Undifferentiated pleomorphic sarcoma (UPS), myxofibrosarcoma, leiomyosarcoma, pleomorphic rhabdomyosarcoma, dedifferentiated liposarcoma, pleomorphic liposarcoma, and angiosarcoma are the major sarcomas that usually demonstrate significant pleomorphism. Pleomorphism versus monomorphism is used by pathologists to narrow down differential diagnoses since sarcomas under these two categories are usually mutually exclusive. When encountering a pleomorphic neoplasm, poorly differentiated carcinoma and melanoma should also be included in the differentials, since most of these tumors also have significant pleomorphism.
A. Undifferentiated pleomorphic sarcoma (UPS)
Was known previously as malignant fibrous histiocytoma (MFH) in the older literature. UPS and high-grade myxofibrosarcoma represent a morphologic spectrum of a single molecular entity. UPS are distinguished based on the percentage of myxoid area with cutoff of 5-10% at most. UPS has a highly variable morphological pattern composed of markedly pleomorphic cells, including bizarre giant cells (Figure 7C). The tumor cells can be spindly, epithelioid, or an admixture of both. Again, myxoid area should be less than 5-10%. By definition, UPS does not demonstrate immunoreactivity to the lineage specific markers listed in the above table as these tumors are completely undifferentiated and have no commitment towards a certain tissue lineage. No recurrent genetic alterations (translocation, mutations) can be used for confirmation of this diagnosis. That is why the diagnosis of UPS is rendered as diagnosis of exclusion from a pure pathological perspective. (Take away: UPS is a pleomorphic tumor that has no other lineage marker positivity. If more than 10% of volume is myxoid matrix, then it is termed a high grade myxofibrosarcoma.)

6. Epithelioid Morphologic Pattern
“Epithelioid” refers to tumor cells that resemble epithelial cells which typically have rounded nuclei, polygonal shape, and moderate to abundant cytoplasm.
A. Epithelioid sarcoma
A rare malignant mesenchymal neoplasm arising in the distal extremities (distal, or conventional type) or proximal extremity/trunk region (proximal type). This is the most common soft tissue sarcoma in the hands. The distal type consists of nodules of epithelioid to plump spindled cells with central geographic necrosis. This morphology can be confused with granulomatous processes (e.g. granuloma annulare). The proximal type (Figure 8A) has a more aggressive clinical course and is characterized by sheets of large pleomorphic epithelioid cells with rhabdoid morphology (large eccentric vesicular nuclei, prominent nucleoli, large eosinophilic paranuclear cytoplasmic inclusion). In keeping with their epithelioid morphology, epithelioid sarcomas show strong immunoreactivity to epithelial markers such as cytokeratins and epithelial membrane antigen (EMA). Most epithelioid sarcomas harbor homozygous deletion/mutations of tumor suppressor gene SMARCB1. Loss of expression of INI1, protein coded by SMARCB1 gene, is usually required to establish the diagnosis. (Take away: Distal extremity tumor with plump spindle cells demonstrating vimentin and cytokeratin/EMA positivity as well as loss of INI1 protein.
B. Clear cell sarcoma of soft tissue
This is a malignant neoplasm typically arising in the deep soft tissues of extremities adjacent to tendons and aponeuroses. It is also referred to as “malignant melanoma of soft parts” due to its melanin pigment production and expression of melanocytic markers (S100, SOX10 and HMB45 etc.). Morphologically, clear cell sarcoma consists of compact nests of monomorphic epithelioid cells separated by fibrous bands (Figure 8B). Tumor cells can often have areas of spindled morphology. Cytologically, most clear cell sarcomas have eosinophilic (pinkish) to amphophilic (staining with both eosin and hematoxylin, blue to grayish) cytoplasm, while clear cytoplasm only accounts for a minority of cases. One important differential diagnosis for clear cell sarcoma is metastatic malignant melanoma since both entities show a morphologic and immunohistochemical overlap. Clear cell sarcoma consistently harbors an EWSR1 gene translocation with various partner genes (ATF1 being the most common one) while malignant melanoma lacks this specific translocation. A FISH study for EWSR1 translocation can be used to reliably distinguish these two types of tumors. (Take away: A deep soft tissue tumor with epithelioid cells with melanin pigment production and an EWSR1 translocation.
7. Round Cell Morphologic Pattern
Refers to tumor with round, uniform nuclei and minimal cytoplasm. This pattern includes “small round blue cell tumors” which confers a very bluish low-power image due to their condensed nuclei (blue stain with hematoxylin), and minimal cytoplasm (pink stain with eosin). Despite their name, small round blue tumor cells are usually larger in size compared to their normal counterparts.
A. Lymphomas
Consist of a large heterogeneous group of neoplasms arising from lymphocytes. Morphologically, lymphomas are composed of sheets of dis-cohesive (e.g. not sticking together) small or large round blue cells without secondary organoid structure such as gland formation etc. (Figure 8C). The cell dis-cohesion, uniform cell-cell distance, and distinct cell borders are morphological features that help distinguish tumors of hematopoietic origin such as lymphomas from carcinomas and sarcomas. The exact classification of lymphomas depends on protein markers by IHC or flow cytometry, as well as underlying genetic alterations. CD markers (Cluster of Differentiation) are one major group of surface proteins used to classify lymphomas. As a rule, to help remembrance, CD markers with numeric numbers< 10 are usually T-cell markers, while numeric numbers > 10 are B-cell markers. CD45 is leukocyte common antigen (a.k.a. LCA) which is very useful as a screening marker.
B. Alveolar rhabdomyosarcoma
Different from other rhabdomyosarcomas described above which predominantly exhibit spindled morphology, alveolar rhabdomyosarcoma is mainly composed of small round blue cells that form alveolar architecture with frequent loss of cell-cell adhesion in the center, resembling alveoli of lung (Figure 8D). Alveolar rhabdomyosarcoma harbors the gene translocation of FOXO1A to PAX3 or PAX7, which can be detected by FISH study or RT-PCR.
C. Mesenchymal chondrosarcoma
This is malignant cartilage tumor located in the skeleton or extra-skeletal soft tissues primarily affecting young adults 15 to 35 years old. Its morphology is characterized by a biphasic pattern composed of primitive small blue round cells and islands of well-differentiated hyaline cartilage (Figure 8E). A prominent hemangiopericytoma-like (staghorn) vascular pattern is often present. The cartilage component may be sparse to absent, particularly on a small biopsy, making accurate diagnosis difficult. There is significant clinical, morphologic and immunohistochemical overlap between mesenchymal chondrosarcoma and Ewing sarcoma. Mesenchymal chondrosarcoma has a specific fusion gene HEY1-NCOA2 which occurs as a as result of translocation and can be used for confirmation of diagnosis. Note that differentiated chondrosarcoma is low grade chondrosarcoma associated with a high-grade spindle cell tumor whereas mesenchymal chondrosarcoma is a low-grade chondrosarcoma associated with a high-grade small, round, blue cell tumor.

8. Intra-articular tumors (no morphologic pattern):
A. Synovial chondromatosis
This is a benign synovial neoplasm characterized by nodules of hyaline cartilage (Figure 9A). Chondrocytes are clustered and mild cytologic atypia, enlargement (plump nuclei), binucleation, and pleomorphism is allowed. Recently, a recurrent FN1-ACVR2A gene rearrangement was identified in about two thirds of synovial chondromatosis, further supporting their neoplastic nature.
B. Tenosynovial giant cell tumors
Benign neoplasm arising from synovium of joints, bursae and tendon sheaths. There are two types, localized and diffuse (the latter also known as pigmented villonodular synovitis), which are identical morphologically. They are characterized by a villous and/or nodular growth pattern composed of four different cell types: mononuclear neoplastic cells, multinucleated giant cells, foamy macrophages, and hemosiderin-laden macrophages (Figure 9B). Mitotic activity can be brisk. The diagnosis is rendered primarily based on histomorphology and clinical information with no specific IHC or molecular study required.

Summary
Consider the morphologic pattern and then the lineage of differentiation as defined by IHC markers. A short summary is reiterated below.
- Lipomatous morphologic pattern
- Benign
- Lipoma- Uniform fat on histology
- Lipoma variants-Mature fat plus a 2nd component
- Angiolipoma-fat plus clusters of capillaries plugged with fibrin thrombi
- Spindle cell lipoma-fat plus bland spindle cells and ropey collagen bundles
- Myelolipoma-fat plus marrow components resembling normal bone marrow
- Hibernoma-brown fat- normal adipocytes with varying numbers of fat cells with small cytoplasmic vacuoles giving a foamy appearance of each cell.
- Intermediate (Locally aggressive)
- ALT/WDL-benign appearing fat with intervening fibrous septa containing hyperchromatic atypical cells and MDM2 (and/or CDK4) amplification.
- Malignant
- Myxoid/round cell liposarcoma-lipoblasts, round cells, myxoid stroma and an arborizing capillary network. It is high grade if the round cell component is more than 5%.
- Dedifferentiated liposarcoma- presence of ALT plus areas dedifferentiated into an undifferentiated tumor with these areas resembling UPS
- Vascular Morphologic pattern
- Benign
- Hemangioma and vascular malformations-benign vascular elements showing CD31 or ERG positivity
- Malignant
- Angiosarcoma-complex anastomosing vascular channels with pleomorphic hyperchromatic cells and CD31 or ERG positivity
- Spindle cell morphologic pattern
- Neural phenotype
- Benign
- Schwannoma-Strong S100 positivity, Antoni A and B areas, palisading nuclei, Verocay bodies and thick-walled blood vessels.
- Neurofibroma-Strong S100 positivity, spindle cells with wavy dark nuclei and collagen bundles that look like shredded carrots
- Malignant
- MPNST-Hypercellular spindle cell sarcoma with marbled-myxoid areas and hope for some S100 positivity.
- Smooth muscle tumors
- Benign
- Leiomyomas-benign appearing elongated spindle cells with cigar shaped nuclei and strong positivity for desmin or smooth muscle actin (SMA).
- Malignant
- Leiomyosarcoma- as above but with pleomorphism, mitoses and necrosis
- Skeletal muscle tumors
- Benign
- Rhabdomyoma- very rare, spindle cells with cross striations as seen in normal striated muscle cells
- Malignant-
- Rhabdomyosarcoma- No easy take away but consider the following: small round blue cell tumors showing skeletal muscle lineage with positive staining for the skeletal muscle markers desmin, myogenin and mMyoD1.Embryonal in children under age 15, alveolar and pleomorphic in older children and young adults.
- Benign
- Benign
- Benign
- Neural phenotype
- Benign
- Benign
- Fibrous tumors
- Benign
- Nodular fasciitis-fast growing spindle cell tumor which mimics malignancy due to its high mitotic rate. FISH demonstrates a USP6 gene re-arrangement.
- Desmoid type fibromatosis-benign appearing spindle cells and abundant collagen with nuclear beta-catenin positivity
- Malignant
- Synovial Sarcoma-both mesenchymal (vimentin) and epithelial (cytokeratin) positivity. Monophasic (if you cannot see an epithelial component but you know it is there in light of cells positive for cytokeratin) or biphasic (you can see spindle cells as well as columnar epithelial structures forming glands), X-18 translocation, SS18-SSX fusion product. TLE1 stain is positive.
- Myxoid morphologic pattern
- Benign
- Myxoma-Benign appearing tumor with few tiny spindle cells and abundant myxoid matrix
- Malignant
- Myxofibrosarcoma- continuum from hypo to hyper cellular with heterogeneous cellularity, pleomorphism and a myxoid stroma. A tumor that looks like UPS but is more than 10% myxoid is a high-grade myxofibrosarcoma
- Pleomorphic morphologic pattern
- Malignant
- UPS-pleomorphic tumor with no other lineage marker positivity, a diagnosis of exclusion
- Epithelioid morphologic pattern
- Malignant
- Epithelioid sarcoma-distal extremity tumor with plump spindle cells demonstrating vimentin and cytokeratin/EMA positivity plus loss of INI1 protein
- Clear cell sarcoma of soft tissues- a deep soft tissue tumor with epithelioid cells with melanin pigment production and an EWSR1 translocation.
- Round cell morphologic pattern
- Malignant
- Lymphoma-sheets of discohesive large or small round blue cells with uniform cell to cell distance and distinct cell borders. CD marker positivity e.g. CD45 (leukocyte common antigen or LCA).
- Alveolar Rhabdomyosarcoma-small round blue cell tumor with translocation of FOXO1A to PAX3 or PAX7.
- Malignant
- Malignant
- Malignant
- Benign
- Benign
- Mesenchymal chondrosarcoma-low grade cartilage juxtaposed with a small round blue cell tumor. Gene fusion is HEY1-NCOA2
- Intra-articular tumors
- Benign
- Synovial chondromatosis-intra-articular nodules of benign or low-grade cartilage plus or minus ossification.
- Tenosynovial giant cell tumor-localized or diffuse, villous and/or nodular growth pattern with spindle cells, multinucleate giant cells, foamy macrophages and hemosiderin laden macrophages.
- Benign
In trying to help the readers remember this list of tumors, I came up with the following mnemonic where each capital letter stands for a specific tumor category.
SLERP a SMall or Medium VaNIla Frosty
- Smooth muscle
- Lipomatous
- Epithelioid
- Round cell
- Pleomorphic
- Skeletal muscle
- Myxoid
- Vascular
- Neural
- Intra-articular
- Fibrous