Synovial Chondromatosis
Primary synovial chondromatosis is a benign condition characterized by cartilaginous metaplasia within the joint synovium leading to the formation of hypercellular cartilaginous nodules. These nodules often detach to become loose bodies within the joint, which may mineralize and ossify over time. Alternatively, synovial chondromatosis may present with a large intra-articular mass of confluent cartilage. Unlike secondary synovial chondromatosis, where loose body formation is degenerative or reactive (such as in cases of arthritis, osteochondritis dissecans, or joint trauma), primary synovial chondromatosis originates from abnormal synovial proliferation.
Primary synovial chondromatosis is typically monoarticular, most commonly affecting the knee, followed by the hip, shoulder, and elbow. Rarely, synovial chondromatosis can involve tendon sheaths in the hands and feet. When loose cartilaginous bodies develop peripheral ossification, the condition may also be referred to as “synovial osteochondromatosis.”
Epidemiology
Synovial chondromatosis is a rare tumor that occurs at least twice as often in men as in women, with most cases presenting between the third and seventh decades of life. While no specific chromosomal abnormalities have been commonly identified in synovial chondromatosis, chromosome 6 aberrations have been observed in a subset of cases.
Clinical Features
The symptoms of synovial chondromatosis typically develop gradually, with patients often experiencing joint pain, stiffness, and sometimes mechanical symptoms, such as joint catching or locking. Effusion or an enlarging mass around the joint may also be observed. One distinguishing feature from tenosynovial giant cell tumor is that the latter is often associated with recurrent atraumatic hemarthrosis, a characteristic not seen in synovial chondromatosis.
Radiologic Features
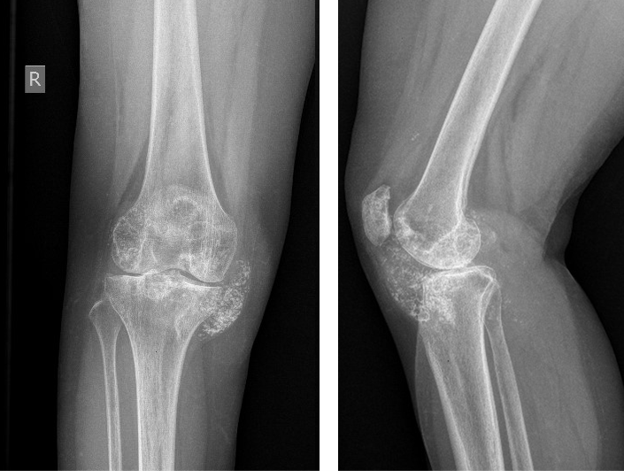
On plain radiographs, multiple calcified bodies may be visible in and around the joint (Figure 1). However, the degree of calcification within these masses can vary significantly, and in 5-30% of cases no calcifications are visible on radiographs due to the masses consisting entirely of a chondroid matrix. In such cases, advanced cross-sectional imaging, such as magnetic resonance imaging (MRI), is necessary to visualize the lesion.
MRI is particularly valuable due to the high water content of the cartilaginous tissue within the loose bodies, which appears as high signal intensity on fluid-sensitive sequences. Calcified areas appear hypointense on both T1- and T2-weighted sequences. Post-contrast MRI often shows heterogeneous enhancement, with a characteristic rim-enhancement pattern typical of cartilage neoplasms. MRI is especially useful when there is extra-articular extension of the tumor, as it allows detailed assessment of the mass’s relationship with surrounding neurovascular structures (Figure 2).

Pathology
Grossly, multiple chondroid or osteochondral bodies are typically observed during surgery, either free-floating within the joint or embedded within the synovium (Figure 3). Microscopically, primary synovial chondromatosis differs from secondary cartilaginous loose bodies associated with trauma, arthritis, or osteochondritis dissecans. The lobular hyaline cartilage nodules characteristic of primary synovial chondromatosis show relative hypercellularity and mild cytologic atypia, with binucleate cells and areas of myxoid change in the matrix. These histologic features give a higher-grade appearance (Figure 4). than that of a simple enchondroma found within the medullary space but are still indicative of a benign lesion in this context.


Differential Diagnosis
Loose bodies are most often encountered as a result of arthritis or trauma. When these causes are excluded, the main differential diagnosis for primary synovial chondromatosis is tenosynovial giant cell tumor. The calcified loose bodies associated with synovial chondromatosis can typically be differentiated from tenosynovial giant cell tumors on plain radiographs. However, when the loose bodies lack calcification and are not visible on x-rays, MRI becomes necessary. On MRI, tenosynovial giant cell tumors often exhibit a characteristic blooming artifact on gradient echo sequences due to hemosiderin deposits within the lesion, while synovial chondromatosis generally appears as more discrete, rim-enhancing loose bodies. Although these imaging features can be helpful, they are not always definitive; thus, tissue diagnosis via needle biopsy or open surgical sampling remains the most reliable method for distinguishing between these two synovial neoplasms.
Other conditions to consider in the differential diagnosis include synovial hemangioma, lipoma arborescens (Hoffa’s disease), and pleomorphic hyalinizing angiectatic tumor. A soft tissue sarcoma arising within a joint must also be considered but is a rare occurrence.
Disease Course: Treatment and Prognosis
Nonoperative management of synovial chondromatosis is generally avoided, as it often leads to further tumor proliferation and eventual joint damage due to the abrasive effect of loose bodies on articular surfaces.
Synovial chondromatosis is typically managed with loose body excision and partial synovectomy of the affected areas. Surgery can be performed using either an open or arthroscopic approach. If clinical and imaging findings are not highly characteristic of synovial chondromatosis, a preoperative biopsy may be necessary before excision. All intra-articular and extra-articular tumors should be excised as thoroughly as possible, with careful attention to preserving nearby neurovascular structures as well as adjacent ligaments, capsule and tendons. Complete excision can be challenging, and the effectiveness of synovectomy in reducing recurrence rates remains debated. Reported local recurrence rates range from 5% to 30% depending on the extent of the synovectomy.
Malignant transformation to chondrosarcoma is rare, but when it does occur, is typically associated with multiple prior recurrences. Neither the size nor the number of loose bodies has been shown to predict local recurrence or malignant transformation. In cases of malignant transformation of synovial chondromatosis to a synovial chondrosarcoma, the treatment is similar to that of conventional chondrosarcoma: resection with wide surgical margins. When limb salvage is not feasible (usually due to extensive tumor involvement of neurovascular structures), amputation may be necessary.
Key Test Topics
- Pathologic differentiation between synovial chondromatosis and pigmented villonodular synovitis.
- Synovial chondromatosis is an example of metaplasia, a transformation of one fully differentiated cell type to another fully differentiated cell type (i.e., synovium to cartilage).